1 MDR-WET
=Common Specifications (CS)
The MDR does not define what it means for a technology to be "well-established". This is not an oversight. For the purposes of the regulation, a formal definition simply is unnecessary. Let’s see why.
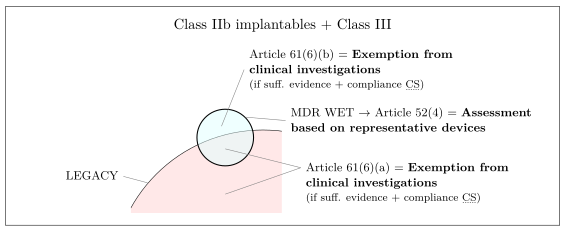
The expression Well-Established Technology (WET) appears in MDR Article 52(5) and Article 61(8). Here it is used in reference to the following class IIb implantable or class III devices: sutures, staples, dental fillings, dental braces, tooth crowns, screws, wedges, plates, wires, pins, clips, and connectors. These devices have been singled out by the European Commission for a more favorable regulatory treatment compared to other class IIb implantable or class III, Figure 1. The advantages include:
-
Assessment based on representative devices (Article 52(4)):
For MDR–WET devices, the technical documentation does not need to be submitted and assessed individually for every device within a generic device group. Instead, a sample or representative device can be used to demonstrate conformity for the entire group. This significantly reduces the regulatory burden and accelerates the conformity assessment process. -
Exemption from mandatory clinical investigations (Article 61(6)(b)):
If the device qualifies as MDR–WET, the manufacturer may be exempt from conducting new clinical investigations, provided that sufficient clinical data already exist. This can lead to significant time and cost savings, particularly for implantable or Class III devices, where clinical investigations are otherwise extensive and resource-intensive.
In the MDR the expression "well-established", therefore, does not explicitly imply any specific technological or clinical status. If we were to infer an MDR definition of well-established technology–which we will refer to as MDR–WET–based solely on these two articles, it would essentially be limited to the following characteristics:
class IIb implantables or class III
explicitely selected by the European Commission
The MDR is also unequivocal on one point: The authority to amend the list of devices that benefit from the favorable treatment lies solely with the European Commission. In other words: Manufacturers of devices other than sutures, staples, dental fillings, dental braces, tooth crowns, screws, wedges, plates, wires, pins, clips, and connectors cannot currently invoke the favourable provisions that specifically reduce the certification burden for these designated devices specified in Article Articles 52(4) and 61(6)(b). Period.
If the MDR is clear on the matter, why did WET become such a hotly debated topic in the field? The controversy began with MDCG 2020-6.
2 MDCG–WET
In 2020, the Medical Device Coordination Group (MDCG) released guidance MDCG 2020-6 outlining a set of characteristics that it considers common to the products specifically mentioned in the MDR—namely, sutures, staples, dental fillings, dental braces, tooth crowns, screws, wedges, plates, wires, pins, clips, and connectors. According to the MDCG, these characteristics are:
relatively simple, common and stable designs with little evolution;
-
their generic device group has well-known safety and has not been associated with safety issues in the past;
-
well-known clinical performance characteristics and their generic device group are standard of care devices where there is little evolution in indications and the state of the art;
a long history on the market.
These properties define what we’ll refer to as an "MDCG–WET". As highlighted in Table 1, the MDCG–WET definition strongly differs from the MDR–WET discussed in the previous section.
| MDR–WET | MDCG–WET |
| Class: Class IIb implantable and Class III devices | Class: Applicable to any class (MDCG 2020-6, page 5); however, the suggested hierarchy of evidence outlined in Annex III of MDCG 2020-6 specifically applies to Class IIb implantable and Class III devices. |
| Legacy status: Applicable to legacy and non legacy devices (MDCG 2020-6, page 5). | Legacy status: Applicable to legacy and non-legacy devices; however, the suggested hierarchy of evidence outlined in Annex III of MDCG 2020-6 specifically applies to legacy devices. |
| Device type: Applicable only to sutures, staples, dental fillings, dental braces, tooth crowns, screws, wedges, plates, wires, pins, clips, and connectors |
Device type: applicable to devices that fulfill the following requirements:
|
Each of the four criteria in the MDCG-WET definition consists of multiple elements—each of requirements which must be demonstrated separately. In Table 2 we illustrates these requirements and propose how to demonstrate MDCG–WET status using documents specific to the device under evaluation (device description, device history, vigilance data), SOTA reviews and meta-analyses (medical background1, meta-analyses or umbrella reviews of device group performance and safety characteristics2), and post-market literature searches focusing on similar devices3.
| Evidence | Criterion 1 | Criterion 2 | Criterion 3 | Criterion 4 |
| SOTA reviews addressing the medical background and the generic device group | ||||
| SOTA medical background | Device group has is considered standard of care | |||
| SOTA device group meta-analysis | Device group has a well-known safety profile |
Device group has:
|
||
| SOTA market analysis |
Device group has:
|
Device group had little change in indications | Device group has long history on the market | |
| Documents specific to the Device Under Evaluation (DUE) | ||||
| Functional specifications | DUE has a simple design | |||
| Device history | DUE has had little change in indications | DUE has a long history on the market | ||
| PSMR/PSUR | DUE not associated with significant safety issues | |||
| Post-market literature searches on similar devices | ||||
| PMCF literature search | Similar devices have not been associated with significant safety issues in the past. |
Below, we analyze how demonstrating MDCG–WET status affects the clinical evidence required for conformity assessment, according to MDCG 2020-6.
First, MDCG 2020-6 focuses on legacy devices—that is, devices certified under MDD or AIMDD. Even if these legacy devices are not yet certified under the MDR, Article 120(3d) requires them to comply with the MDR’s post-market surveillance requirements. This means that legacy devices must have PMS data at their disposal—for example, complaints and vigilance data. According to the definition in Article 2(48) of the MDR, such PMS data qualify as "clinical data" and—as we know from Article 61(1)—clinical data form the basis for demonstrating conformity with the relevant s in the clinical evaluation. So does this mean that legacy devices automatically possess the data required for certification under the MDR? MDCG 2020-6 (pages 17 and 21) provides a clear answer to this question: regardless of the device type, complaints and vigilance data may only support other forms of clinical evidence—reliance on such data alone is not sufficient.
Note that this requirement is not explicitly stated in the MDR. The regulation merely states that PMS data—including complaints and vigilance data—are considered clinical data. As such, the threshold set out in MDCG 2020-6 represents an interpretation by the MDCG. However, in practice, you can expect most notified bodies to align with the MDCG interpretation.
According to MDCG 2020-6, therefore, manufacturers of legacy devices must provide clinical data from additional sources beyond complaints and vigilance data. The question that now arises is: which additional data, and from which sources?
As is often the case, neither the MDR nor the MDCG guidance can tell you exactly which type of data constitutes sufficient clinical evidence for your specific device. This is not due to a lack of willingness, but because too many parameters influence the choice and adequacy of data—device type, clinical context, risk classification, and more. For this reason, the regulations and guidances can only define the minimum requirements—that is, what is clearly not sufficient. This is also precisely what MDCG 2020-6 does for Class IIb implantable and Class III devices.
According to MDCG 2020-6, Class IIb implantable and Class III devices that do not qualify as MDCG–WET cannot rely solely on "low level" clinical data to demonstrate conformity with the General Safety and Performance Requirement (GSPR). Instead, these devices must be supported by what the MDCG calls “Rank 1 to 4” data. This includes:
-
High quality clinical investigations covering all device variants, indications, patient populations, duration of treatment effect, etc
High quality clinical investigations with justifiable gaps
High quality clinical data collection systems such as registries
-
Outcomes from studies with potential methodological flaws but where data can still be quantified and acceptability justified4.
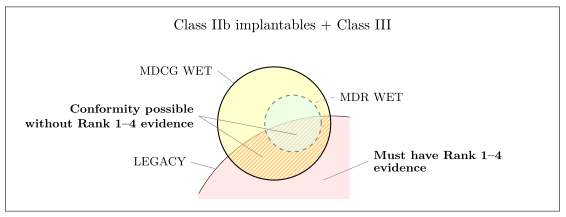
Note that the requirement that Class IIb implantable and Class III devices which do not qualify as MDCG–WET must be supported by Rank 1–4 clinical evidence is not specified in the regulation itself but is introduced in the MDCG 2020-6 guidance as a form of "best practice"—and, indeed, one that most notified bodies are likely to follow. It is also important to emphasize that this requirement does not mean all clinical evidence for a device must come from the top-ranked sources and it does not exclude the use of lower-ranked evidence to support or complement a submission.
In a nutshell, Figure 2, the core benefit of demonstrating MDCG–WET status is that, for Class IIb implantable and Class III devices, this strategy may open the door to basing the demonstration of conformity on lower-level clinical data—such as Rank 5 (data from equivalent devices), Rank 7 (complaint and vigilance data), or Rank 8 (proactive post-market surveillance data)—even though reliance on such levels of evidence is typically accepted only for lower-risk device classes.
It is important to emphasize that while MDCG 2020-6 acknowledges the use of supporting evidence such as clinical data from similar devices (Rank 6), compliance with non-clinical elements of common specifications (Rank 10), and other forms of non-clinical data—including preclinical studies, simulations, and engineering data (Ranks 11 and 12)—it does not suggest that conformity for MDCG–WET devices can be demonstrated on the basis of these sources alone. On the contrary, it explicitly states that, in line with Article 61(1) of the MDR, the demonstration of conformity with the GSPRs must be based on clinical data generated with the device under evaluation or an equivalent device.
For devices in risk classes lower than Class IIb implantable and Class III, the benefit of demonstrating MDCG–WET status becomes less pronounced. It is important to highlight that Article 61(1) of the MDR simply requires that conformity with the relevant GSPRs be demonstrated on the basis of sufficient clinical evidence—leaving it to manufacturers to justify what constitutes “sufficient,” in light of the state of the art in medicine. In general, the MDR does not prohibit the use of lower-ranked evidence to support a demonstration of conformity, provided that the approach is adequately justified. Similarly, the MDR allows cumulative approaches to clinical evidence. In fact, clinical validation is inherently cumulative: it builds on preclinical data and information from similar devices, gradually progressing toward a full demonstration of conformity using multiple sources of evidence. The lower the device’s risk class, the more likely notified bodies are to accept flexible, risk-based approaches.
References
-
AIMDD — Council Directive 90/385/EEC of 20 June 1990 on the approximation of the laws of the Member States relating to active implantable medical devices (AIMDD). Council of the European Communities, 1990
-
MDCG 2020-6 — Regulation (EU) 2017/745: Clinical evidence needed for medical devices previously CE marked under Directives 93/42/EEC or 90/385/EEC. MDCG, 2020
-
MDD — Council Directive 93/42/EEC of 14 June 1993 concerning medical devices (MDD). Council of the European Communities, 1993
-
MDR — Regulation (EU) 2017/745 on medical devices. European Parliament and Council of the European Union, 2024
-
Medical Background SOTA — Ho to conductd medical background SOTA analyses. 4BetterDevices GmbH, 2025
-
POST-MARKET SEARCHES — How to conduct post-market searches. 4BetterDevices GmbH, 2025
-
SURVEYS — When are surveys clinical investigations?. 4BetterDevices GmbH, 2024
-
See our guide on Medical Background SOTA.↩︎
-
Guide coming soon.↩︎
-
See our guide on POST-MARKET SEARCHES.↩︎
-
For more on Rank 4 evidence—specifically, high-quality surveys—see our guide SURVEYS.↩︎